
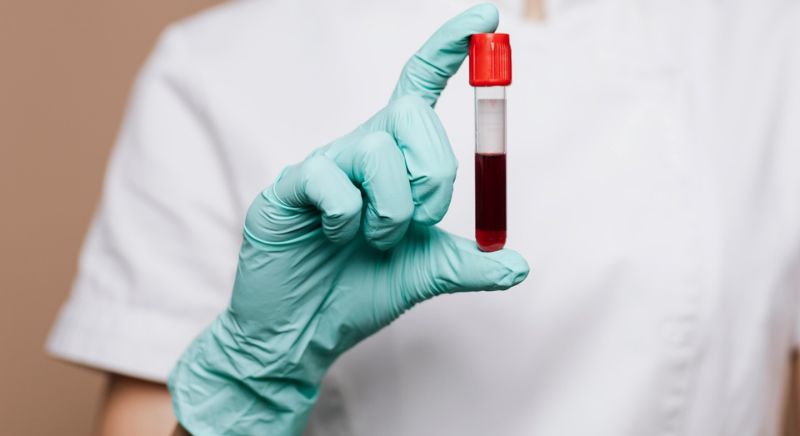
When symptoms are vague or persistent—fatigue, dizziness, unexplained weight change, low mood, recurrent infections, concentration problems—patients often expect a diagnosis immediately. In reality, diagnosis in primary care is usually a staged process. A GP starts with history and examination, then selects investigations that can efficiently narrow possibilities. Blood tests are among the most useful of those tools.
Early blood testing does not mean “test everything.” It means using targeted laboratory data at the right stage, so decisions about monitoring, treatment, referral, or reassurance are based on evidence rather than guesswork. This guide explains why GPs request blood tests early, what different panels can contribute, how results should be interpreted, and how patients can navigate diagnostic care in Central London more confidently.
Early testing is often a strategy for reducing uncertainty safely. In many presentations, symptoms alone are non-specific and overlap across multiple conditions.
Blood tests do not replace consultation—they strengthen it.
Different test groups answer different questions. Understanding this reduces anxiety about isolated numbers.
An FBC can help assess red cells, white cells, and platelets. It may support investigation of fatigue, infection patterns, inflammatory states, bleeding tendencies, or anaemia-related symptoms.
In non-specific presentations, a full blood count testing pathway is often a first-line component because it provides broad baseline information quickly.
Thyroid hormones influence metabolism, temperature regulation, mood, and energy. Symptoms of thyroid dysfunction can mimic many other problems.
Where endocrine causes are plausible, thyroid blood test options may be considered as part of a broader panel rather than as a stand-alone answer.
Liver-related markers may assist assessment in medication monitoring, alcohol-related risk review, persistent fatigue, or abdominal symptom work-up.
When clinically relevant, liver function blood testing may be requested alongside metabolic and inflammatory markers to improve interpretation context.
Fasting glucose and/or HbA1c can support diabetes and prediabetes assessment, especially when symptoms, family history, or weight trends raise suspicion.
These can guide hydration assessment, medication safety, BP management, and chronic disease monitoring.
Markers like CRP/ESR can suggest inflammatory activity, but they are non-specific and must be interpreted with history and examination.
Ordering tests too late can delay diagnosis; ordering broad untargeted tests too early can generate incidental findings without improving care.
The best timing usually sits between those extremes:
This is especially important when symptoms are persistent but not yet severe.
Many people receive a result and assume it is either “normal = nothing wrong” or “abnormal = definite disease.” Both assumptions can be misleading.
Self-referral testing can improve access for some patients, especially for monitoring or pre-consultation preparation. GP-led testing often offers stronger contextual interpretation and continuity.
If comparing options, reviewing private blood test categories and pathways can help patients understand scope and follow-up structure before booking.
A broad initial panel may help assess anaemia, thyroid, glucose, liver/kidney context, and inflammatory patterns. Interpretation should still include sleep, mental health, lifestyle, and medication review.
Bloods may support evaluation of anaemia, hydration/electrolytes, and metabolic contributors while clinical examination checks cardiovascular and neurological context.
Testing can help examine thyroid, glucose regulation, inflammatory signals, and organ function while history explores appetite, stress, GI symptoms, and medication effects.
Some long-term medicines require periodic blood monitoring for safety and efficacy; delaying these checks can increase risk.
Very broad panels can create low-value abnormalities and anxiety. Test choice should answer focused clinical questions.
Waiting too long can delay interventions that are simpler earlier in the disease pathway.
Balanced, clinically guided timing is usually safest.
Patients can improve result quality and consultation efficiency by preparing:
Ask in advance whether fasting is necessary; non-fasted results may still be appropriate for many tests, depending on clinical purpose.
A good post-result process typically includes:
Patients should leave with explicit safety-net advice: what to watch, when to re-contact, and when urgent care is needed.
Repeat testing is not a sign of failure; it is often part of good clinical method. A GP may repeat tests when:
Typical repeat intervals vary by context and urgency. The key is to avoid two extremes: repeating everything too often without reason, or delaying necessary reassessment when symptoms are evolving.
Pre-test probability means estimating how likely a condition is before testing, based on symptoms, history, age, risk factors, and examination. This helps clinicians choose tests with better diagnostic yield.
Why this matters:
For patients, this is useful to remember: a “smaller” test set is not necessarily less thorough if it is better matched to your presentation.
Digital access to results is useful, but reading numbers without context can increase anxiety.
Practical approach:
Helpful questions include:
If you are arranging private or mixed-route diagnostics, check these operational points before booking:
This planning reduces delays and prevents fragmented care.
Sometimes bloods are necessary but not sufficient. Depending on symptoms, your GP may also consider:
That does not mean blood tests were unhelpful. It means they were one component in a staged diagnostic pathway.
Because many symptoms overlap across conditions. A grouped panel can narrow possibilities efficiently while reducing repeat appointments and delayed decision-making.
Not always. Normal tests are reassuring, but they do not rule out every diagnosis. Ongoing or worsening symptoms still need clinical reassessment.
It can be useful in some cases, but only if follow-up interpretation is clear. Without context, results may confuse rather than clarify.
Usually not. Many mild abnormalities are transient or low significance. Repeat testing and clinical context determine whether action is needed.
No. They are one component of diagnosis, alongside history, examination, and sometimes imaging or specialist review.
Promptly. If symptoms escalate—especially chest pain, breathlessness, confusion, severe dehydration, or neurological changes—seek urgent care regardless of pending routine follow-up.
Early blood testing works best when it is targeted, interpreted in context, and linked to a clear action plan. The most useful test is not the biggest panel—it is the one that helps answer the right clinical question at the right time.
This article provides general educational information and is not a diagnosis or personal treatment recommendation. Online guidance cannot replace professional advice tailored to your dental history and symptoms. If pain, bleeding, sensitivity, swelling, or visible oral changes persist, seek assessment from a registered dental professional.
Written Date: 18 September 2026 | Next Review Date: 18 September 2027
Why do GPs ask about oral health in diabetes and c...

Understand what executive health assessments can a...

Unsure whether to book a GP appointment or use a w...

Explore how oral inflammation and wider health can...

Understand common causes of gum sensitivity and pr...
Wondering why your GP recommends blood tests early...

5 AVE MARIA LANE, ST PAUL'S, LONDON EC4M 7AQ
Mon - Fri 9AM - 6PM
Sat - Sun 10AM - 2PM
All tests and screenings are booked online or by phone — no referral and no registration needed. Same-day appointments are usually available.
2026 © PRIVATEGPS.LONDON. All rights reserved.